Psilocybin changes perception, emotion and the organisation of brain activity through its active metabolite, psilocin. Research can now describe several stages of this process, from receptor binding to changes in communication between brain networks. Explaining an altered state is nevertheless different from explaining why a particular patient achieves lasting recovery.
Receptor activity describes a drug’s initial biological action. Network measurements describe patterns of brain activity. Clinical outcomes describe changes in symptoms and functioning. Evidence at one level can inform the others, but cannot substitute for them.
On this page
From psilocybin to psilocin
Psilocybin acts largely as a prodrug: it is converted into psilocin, the compound responsible for its principal psychoactive effects. Psilocin concentrations rise and fall over hours. This matters when considering reports of effects lasting weeks or months: a persistent clinical change does not mean that an active psychedelic concentration remains in the brain for that period.1
The distinction also separates acute intoxication from subsequent learning, adaptation and recovery. A short pharmacological exposure might initiate a longer process, but the duration of that process cannot be read directly from the drug’s elimination time. Nor does the disappearance of the acute experience establish that every subsequent effect will be beneficial.
Serotonin receptors and the altered state
Psilocin interacts with serotonin receptors, with the 5-HT2A receptor playing a central role in its psychedelic effects. In a human positron emission tomography study, eight volunteers received psilocybin, and receptor occupancy was related to plasma psilocin and reported subjective intensity. This provides direct evidence connecting pharmacology with the altered state.2
Occupancy describes the proportion of receptors engaged under the measurement conditions. It is not a measure of how much healing has occurred. The study did not establish a receptor-occupancy target for treating an individual patient’s depression, trauma symptoms or addiction. Greater subjective intensity should therefore not be equated with a greater probability of clinical benefit.2
Receptor language can otherwise become misleading shorthand. A psychiatric disorder is not diagnosed by assuming that a single receptor is underactive, and activating that receptor does not establish that the underlying disorder has been corrected. The consequences depend on the cells and circuits involved, the person’s condition and the context in which the experience occurs.
Brain networks become differently organised
Functional connectivity describes statistical relationships between activity recorded in different brain regions. In functional MRI, these relationships are inferred from blood-oxygenation signals; they are not direct observations of individual synapses or proof that two regions are sending a particular message to each other. Connectivity is also different from the physical wiring of the brain.
A 2024 study repeatedly scanned seven healthy adults around psilocybin and methylphenidate sessions. Psilocybin produced marked changes in network organisation, including reduced synchrony within usual patterns. Most changes were acute, while reduced connectivity between the anterior hippocampus and default mode network persisted for weeks. These observations concern a small, intensively measured healthy sample, not a demonstration that a network change caused recovery from depression.3
The default mode network participates in processes involving internally directed thought and aspects of self-related cognition. Describing it as an ego centre that is switched off oversimplifies both the anatomy and the experience. A change in its relationship with other networks does not imply that ordinary selfhood has been removed or that an undesirable part of the brain has been repaired.
Context changes the meaning of a brain signal
Network changes are not adequately captured by a single claim that the brain becomes disordered. A 2026 investigation of 62 participants without previous psychedelic experience varied contexts including rest, meditation, music and film. Its analyses identified structured patterns aligned with context, associated with features of subjective experience and next-day mindset change.4
This adds a useful qualification to descriptions of desynchronisation: an average measure can conceal organisation that becomes visible when time and context are considered. It does not establish that a particular playlist, meditation practice or therapy setting produces superior clinical outcomes. The observations generate clinical hypotheses rather than a validated treatment prescription.4
A person listening to music, recalling a distressing event or feeling unsafe is not engaging with an interchangeable background. The setting is part of what the person is experiencing. Clinical preparation and professional boundaries therefore remain relevant even when the immediate explanation of the altered state begins with receptor pharmacology.

Neuroplasticity: promising biology with important limits
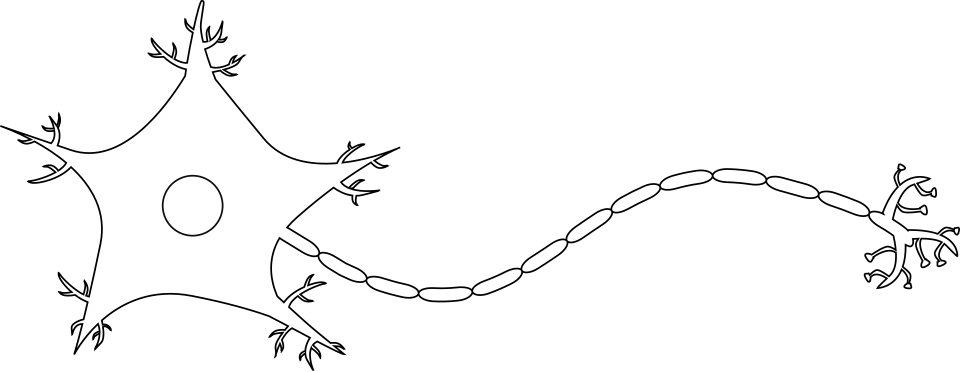
Neuroplasticity refers to the capacity of nervous tissue and its activity to change. It includes several distinct phenomena; a change in a synaptic structure, a pattern of connectivity and a learned behaviour are not interchangeable measures.
In a mouse study, a single psilocybin exposure increased the size and density of dendritic spines in frontal cortex by approximately 10%. Some structural changes remained a month later. Dendritic spines are small protrusions involved in many excitatory synaptic connections. These findings support a biological capacity for lasting structural change, but do not demonstrate the growth of new neurons or the repair of a human psychiatric disorder.5
Further mouse work implicated particular pyramidal cell populations and their 5-HT2A receptors in lasting structural and behavioural effects. Such experiments can test mechanisms more directly than human imaging, while still leaving a substantial translational gap. Results from a defined animal model cannot identify the best treatment for an individual patient.6
Plasticity also has no automatic therapeutic direction. The capacity to change does not specify what is learned, whether it is useful or whether it persists under later stress. A claim that the brain is more changeable needs to be followed by a clinical question: change towards what outcome, for whom and under which conditions?
| Observation | What it helps explain | What it does not establish |
|---|---|---|
| Serotonin receptor occupancy | Drug engagement with a biological target | An individual therapeutic target or a cure |
| Altered functional connectivity | Changes in patterns of brain activity | Permanent rewiring or tissue repair |
| New dendritic spines in animals | A possible substrate for plasticity | Human neurogenesis or clinical recovery |
| Correlation with subjective intensity | A relationship between experience and measurement | That greater intensity produces greater benefit |
Why a compelling mechanism is not enough
A proposed therapeutic mechanism should explain changes that matter to patients, including reduced symptoms and improved functioning. A correlation between a scan measure and improvement is a starting point. It may reflect a causal pathway, a consequence of improvement or another factor affecting both measurements.
Comparative clinical trials are needed to establish the value of the whole intervention. Mechanistic studies can then help investigate which components contribute and why responses vary. Psychological support, expectation, the acute experience and subsequent care may interact with the pharmacological effects; their contributions should not be dismissed simply because a biological change is measurable.7
Equally, an emotionally meaningful experience need not be translated into an elaborate neuroscientific explanation to be taken seriously. Personal meaning and clinical benefit can overlap, but neither is a direct readout of a scan. A patient can report an important experience while continuing to require treatment for the original condition.
What this means in clinical practice
Current mechanistic findings support careful investigation and informed discussion. They do not provide a validated scan-based method for choosing a patient’s dose, predicting response or deciding when to repeat treatment. Claims of a universal brain reset go beyond what these methods demonstrate.
The useful clinical account joins biological findings with measured outcomes and the person’s circumstances. It asks whether improvement lasts, what adverse effects occur and whether ordinary life becomes more manageable. Receptors and networks help explain how change may become possible; follow-up establishes whether that possibility became a useful and sustained result.
References
- Otto ME, van der Heijden KV, Schoones JW, et al. Clinical Pharmacokinetics of Psilocin After Psilocybin Administration: A Systematic Review and Post-Hoc Analysis. Clin Pharmacokinet. 2025;64:53-66. doi:10.1007/s40262-024-01454-4.
- Madsen MK, Fisher PM, Burmester D, et al. Psychedelic effects of psilocybin correlate with serotonin 2A receptor occupancy and plasma psilocin levels. Neuropsychopharmacology. 2019;44:1328–1334. doi:10.1038/s41386-019-0324-9.
- Siegel JS, Subramanian S, Perry D, et al. Psilocybin desynchronizes the human brain. Nature. 2024;632:131-138. doi:10.1038/s41586-024-07624-5.
- Stoliker D, Novelli L, Khajehnejad M, et al. Psychedelics align brain activity with context. Nature. 2026;656:936–947. doi:10.1038/s41586-026-10910-z.
- Shao LX, Liao C, Gregg I, et al. Psilocybin induces rapid and persistent growth of dendritic spines in frontal cortex in vivo. Neuron. 2021;109:2535–2544.e4. doi:10.1016/j.neuron.2021.06.008.
- Shao LX, et al. Psilocybin’s lasting action requires pyramidal cell types and 5-HT2A receptors. Nature. 2025;642:411–420. doi:10.1038/s41586-025-08813-6.
- Hosein MM, Reid MJ, Walser S, et al. Considerations and cautions for the integration of psilocybin into routine clinical care: a consensus statement from the US National Network of Depression Centers' Task Group on Psychedelics and Related Compounds. EClinicalMedicine. 2025;89:103517. doi:10.1016/j.eclinm.2025.103517.