Cannabis can feel calming to one person and provoke anxiety or panic in another. CBD has shown promising effects in some experiments, but neither those findings nor reports of relief establish cannabis as a standard treatment for anxiety disorders or PTSD. The product, dose, context and diagnosis all matter.
Evidence checked: 1 October 2026. This article provides general information. Persistent anxiety, trauma symptoms or adverse mental effects need assessment by a qualified healthcare professional.
Relief is important, but the target needs to be clear
“Anxiety” can describe temporary stress, generalised anxiety disorder, panic attacks, social anxiety or symptoms associated with trauma. These are not interchangeable research populations. A treatment that reduces discomfort during one laboratory task may not reduce avoidance, recurrent panic or the disability associated with a long-standing disorder.
When someone reports benefit, ask what changed: bodily tension, intrusive thoughts, sleep, confidence outside the home or distress during a particular activity. That description is more useful than a general claim that cannabis treats anxiety. Sustained functioning matters alongside immediate relief.
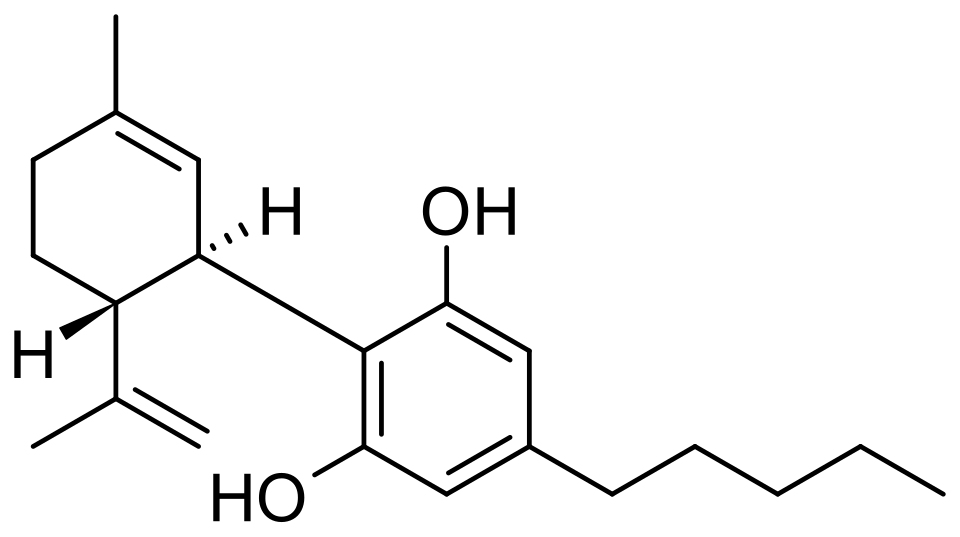
CBD (cannabidiol)
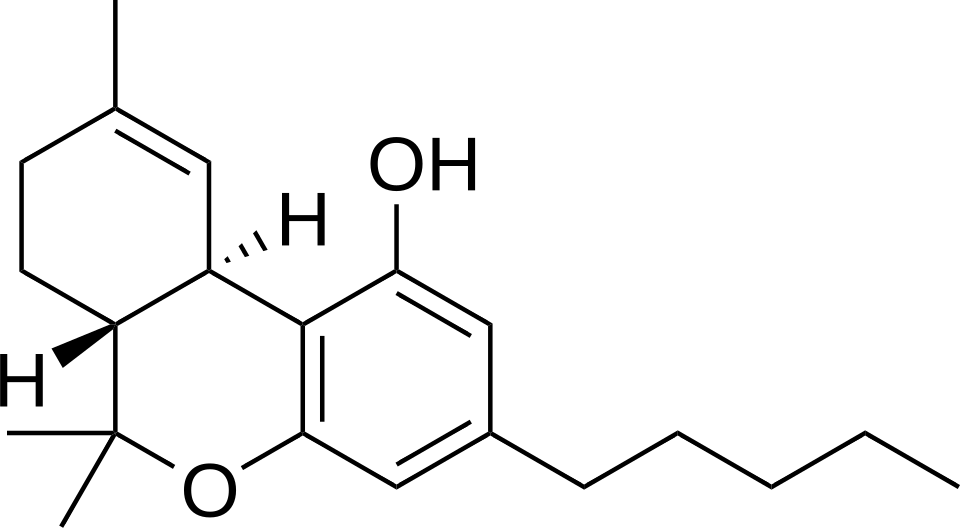
Delta-9-THC


CBD: promising experiments and important limits
A 2011 study in social anxiety randomly allocated 24 treatment-naïve patients to a single CBD dose or placebo before simulated public speaking. Several anxiety-related measures favoured CBD. This was a small, single-session experiment; it did not establish an effective long-term regimen or validate low-dose retail products.
Findings differ across experimental tasks. A controlled study of 61 healthy young adults found no CBD effect on fear, panic symptoms or heart rate during a carbon-dioxide challenge. It was published online in 2022 and appeared in a 2025 journal issue. This does not negate the social-anxiety experiment, but it shows that “CBD reduces anxiety” is not a result that can be assumed in every setting.
A 2025 trial of stressed students also found no advantage of CBD oil over placebo oil across its measured outcomes. Improvements after starting a product can be real while still requiring a comparison group to establish what caused them.
What newer naturalistic research adds
A 2026 study of 345 adults seeking anxiety relief tracked daily symptoms while participants used assigned cannabinoid product types in ordinary life. Anxiety declined over the study, with patterns differing between flower, edible products and cannabinoid composition. This offers useful detail about experiences outside the laboratory.
It should not be interpreted as a blinded demonstration that cannabis treats a diagnosed anxiety disorder. Participants wanted to use cannabis, products were used as needed, and the design was naturalistic. The findings support further controlled research and more precise product descriptions. They do not establish a universal “best strain for anxiety”.
THC can also make anxiety worse
THC may cause racing thoughts, panic, suspiciousness or perceptual changes. The fact that an earlier experience was pleasant does not guarantee the next will be. Potency, quantity, previous exposure and the surrounding situation can all influence the experience. Health Canada describes both the desired and unwanted mental effects.
These effects matter particularly when treatment is being sought for fear or hypervigilance. A medicine that occasionally produces severe panic may be a poor trade-off even if it gives temporary relief on other occasions. Adding CBD cannot be relied on to neutralise THC, and a reassuring strain name is not a substitute for clinical monitoring.
PTSD requires its own evidence
PTSD includes symptoms such as re-experiencing, avoidance and a persistent sense of threat. Improved sleep or fewer remembered dreams does not necessarily mean that the disorder as a whole has improved.
In a 2021 randomised trial involving 80 military veterans in its first stage, three smoked cannabis preparations were compared with placebo over three weeks. All groups improved, but no active preparation significantly outperformed placebo on the primary PTSD outcome. The trial was brief and preliminary; it also does not justify smoking cannabis as a UK medical route.
The 2023 US VA/DoD guideline recommends against cannabis for PTSD, reflecting insufficient evidence of efficacy and concerns about harm. This is US guidance, not a statement of UK prescribing law. It is nevertheless an important evidence-based counterweight to claims that cannabis is an established trauma treatment.
What established treatment offers
NICE guidance for generalised anxiety and panic supports a stepped approach, including appropriate psychological treatments and, when indicated, medication such as an SSRI. The choice should reflect diagnosis, severity, previous response and the person’s preferences. For PTSD, evidence-based trauma-focused treatment remains central; the VA/DoD guideline describes effective options.
A discussion of cannabis should therefore include whether the person has had access to an appropriate treatment, not just whether they have received any counselling or any antidepressant. Therapy aimed at general support is not necessarily the same intervention as a structured treatment tested for a particular disorder.
How to discuss cannabis use without stigma
People may avoid telling clinicians about cannabis because they expect disapproval. That makes assessment harder. An honest account of prescribed and non-prescribed use helps identify interactions, changes in symptoms and difficulties reducing use. The aim is to understand what is happening and improve care.
If a specialist considers a cannabinoid trial, useful goals include less avoidance, fewer disruptive episodes and better participation in daily life. Monitor anxiety between doses as well as shortly afterwards. Review increasing reliance, unwanted mental effects and whether the treatment interferes with other care. A feeling of immediate calm is one outcome, not the whole assessment.
When to seek prompt help
New hallucinations, marked paranoia, severe confusion or rapidly worsening mental health need prompt medical attention. Where there is immediate danger, seek emergency help. Do not treat a serious reaction as evidence that a different commercial strain should simply be tried. A previous history of psychosis or other significant mental illness belongs in the prescribing assessment.
The present evidence supports careful investigation and individual assessment. It does not support presenting cannabis as a broadly established solution for anxiety or trauma-related disorders.